

Prediction Markets Are Creating a New Risk for Pharmaceutical Vendor Contracts
Prediction markets tied to clinical trials, regulatory decisions, and other pharmaceutical events are creating new questions for vendor contracts and confidentiality provisions. This article looks at what pharmaceutical and life sciences companies may want to review in their agreements and compliance policies.
Prediction markets are creating a new compliance issue for pharmaceutical companies.
Platforms now allow users to trade on events such as regulatory decisions, clinical trial outcomes, and other company specific developments. That creates a simple problem: people outside the company may have access to sensitive information before the market does.
In pharma, that can include CROs, laboratories, consultants, data vendors, clinical partners, and other service providers.
The risk is not limited to disclosure. Someone could use nonpublic information to place a position on an event tied to a clinical trial, FDA decision, regulatory milestone, or commercial development without ever sharing the information with anyone else.
That means companies should review whether their contracts restrict not only disclosure, but also the use of confidential information for prediction markets, event contracts, wagering, or similar financial activity.
What companies should review
Pharmaceutical and life sciences companies may want to look at:
confidentiality provisions
vendor agreements
consulting agreements
clinical services contracts
internal compliance policies
reporting and investigation rights
termination rights tied to misuse of information
The issue is straightforward. Contracts written years ago may not address the ways confidential information can be monetized today.
Clinical and regulatory information can have significant value before it becomes public. As prediction markets grow, legal and compliance teams should make sure their agreements reflect that reality.
Lanton, Lanton & Sosa Law PLLC advises pharmaceutical, healthcare, and life sciences companies on contracts, regulatory issues, vendor relationships, compliance, and commercial risk.
For a deeper discussion, see the recent PharmExec article:
Prediction Markets Expose a Gap in Pharmaceutical Vendor Contracts
https://www.pharmexec.com/view/prediction-markets-expose-gap-pharmaceutical-vendor-contracts

340B Rebates: Who Bears the Cost of Changing How the Program Works?
HRSA's revised 340B rebate pilot raises new questions about drug purchasing, cash flow, transaction verification and administrative costs. This article examines the concerns of manufacturers and hospitals, the pilot's regulatory safeguards, and the financial, legal and operational considerations facing covered entities, pharmacies and their service providers.
Why the 340B Program Matters
Congress established the 340B Drug Pricing Program in 1992 to help eligible healthcare organizations stretch scarce resources and serve patients. Under the program, manufacturers participating in Medicaid and Medicare Part B agree to provide qualifying outpatient drugs at or below a statutory ceiling price to eligible hospitals, health centers and other providers known as covered entities. The program has generally delivered that price through an upfront purchasing discount. [1]
That purchasing arrangement is now embedded in many organizations’ pharmacy operations. Covered entities use 340B savings in different ways, which can include supporting medication access, specialty services and care for patients who may face barriers to treatment. The program is also operationally complex: hospitals and clinics may use in-house or contract pharmacies, wholesalers, inventory replenishment systems and third-party administrators to determine which transactions qualify.
The 340B statute prohibits diversion of discounted drugs to ineligible patients and duplicate discounts involving Medicaid rebates. Determining which transactions qualify and identifying overlapping price concessions have become persistent administrative questions as the program and pharmaceutical distribution arrangements have grown. [1]
HRSA’s revised rebate pilot is designed to test whether a rebate-based approach addresses these administrative questions more effectively than the existing upfront-discount model. It applies to a limited set of drugs, rather than changing 340B purchasing across the program. [1, pp. 48,894–48,896]
Why Manufacturers Are Interested in a Rebate Model
Manufacturers have argued that an upfront discount can make it difficult to verify the specific transaction that ultimately qualifies for 340B pricing. They have sought greater visibility into claims data to identify duplicate discounts, evaluate eligibility and reconcile overlapping requirements across federal drug-pricing programs. For selected Medicare-negotiated drugs, the pilot also addresses potential overlap between 340B discounts and Medicare Maximum Fair Price (MFP) discounts; these price concessions are not cumulative. [1, pp. 48,884–48,886]
Supporters of rebate-based arrangements contend that linking payment to a validated dispensing or administration record could improve claims-level transparency and reduce the need to identify problems only through retrospective audits. They also argue that covered entities and their administrators already collect much of the information that would be used for reporting. [1]
Those arguments do not resolve every implementation issue. More transaction data raises questions about the information manufacturers may receive, permitted uses of that information, privacy, platform governance and the cost of producing and verifying claims. Whether the anticipated benefits materialize is part of what the pilot is designed to examine.
What the Revised Pilot Would Actually Change
In July 2026, the Health Resources and Services Administration announced a revised, voluntary pathway for qualifying manufacturers to provide 340B pricing through rebates instead of upfront discounts. The pilot is limited to selected drugs in the Medicare Drug Price Negotiation Program with initial price applicability years 2026 and 2027, during their applicable pricing periods. HRSA estimates that the included products represent less than 5.5% of total 340B sales, based on 2025 data. The rest of the program would continue using upfront discounts in 2027. [1, pp. 48,893–48,894; 2]
For an approved participating product, the covered entity would order through existing distribution channels at wholesale acquisition cost (WAC). Following an eligible dispense or administration, it would submit specified transaction information. The rebate would equal WAC minus the applicable 340B ceiling price on the day of dispense and would be paid at the unit level. This means the financial benefit arrives through a separate transaction rather than being reflected in the initial acquisition price. [1]
The revised framework includes several operational safeguards. Manufacturers must fund the required submission platforms and provide technical assistance. Their approved plans must allow at least 90 calendar days’ notice before implementation, and covered entities must have at least 45 calendar days after dispensing to submit data, with specified allowances for exceptions. Manufacturers must pay the rebate or issue a documented denial within ten calendar days after receiving a complete submission. An incomplete submission can restart that payment clock when the missing information is supplied. [1]
The pilot is scheduled to begin January 1, 2027, for manufacturers whose rebate plans receive HHS approval. It does not change purchasing for products outside its limited scope. [1]
Why Hospitals Are Concerned
Hospitals and health systems have raised concerns about the effect of moving from a known upfront acquisition discount to a later rebate. One issue is liquidity: an organization may need to purchase a high-cost drug at WAC, hold it in inventory, dispense or administer it, submit transaction information and wait for a validated rebate. Even a ten-day payment requirement begins after a complete submission, not necessarily on the purchase date. [1]
Covered entities have also pointed to potential administrative costs, including staff training, system changes, reconciliation, disputed transactions and changes to wholesaler credit arrangements. Their concern is not limited to whether a rebate ultimately arrives. For some hospitals, uncertainty or new financing costs could affect resources used to maintain services, including medication access and other programs serving vulnerable patients. Those effects would differ by facility and cannot be inferred from a uniform estimate. [1]
HRSA takes a different view of the likely financial impact. It expects the ten-day deadline, unit-level rebates and existing wholesaler payment windows to allow many organizations to receive rebates before their wholesaler invoices become payable. The agency also expects existing pharmacy systems and third-party administrators to absorb much of the additional work, although it acknowledges that some covered entities may need new resources. [1]
The two positions turn in part on actual purchasing arrangements. A rebate paid before the relevant wholesaler invoice is due may create little additional financing expense. A different experience is possible when inventory moves slowly, submissions are incomplete, credit terms are tight or reconciliation is difficult. The pilot’s practical effects will need to be assessed across different provider types and purchasing models.
Who Bears the Financial and Administrative Costs?
The answer is not a single stakeholder. The revised pilot assigns some obligations explicitly, while other costs depend on how organizations purchase drugs, operate their systems and contract with service providers.
Participant
Responsibility or potential exposure
Manufacturers
Fund the required data-submission platforms; validate eligible submissions; pay or document denials on time; provide technical assistance and required reporting.
Covered entities
Manage purchasing and eligible-claim submissions; reconcile rebates; potentially absorb internal system, training, staffing and working-capital costs.
Third-party administrators and technology vendors
Perform data extraction, submission, monitoring and reconciliation under their contracts; compensation and liability for additional services depend on those agreements.
Wholesalers
Existing invoice, credit and payment terms influence whether the covered entity receives its rebate before the acquisition invoice is due.
HRSA estimates an average annual claims-reporting cost of approximately $34,320 per covered entity under its information-collection analysis, with actual costs varying by entity type. This is an average regulatory estimate, not a prediction of what any particular hospital will spend. Manufacturers are required to fund the submission platforms, but that does not necessarily cover all costs of a covered entity’s internal preparation, integration, monitoring or dispute management. [1, pp. 48,892–48,894]
The contractual questions follow naturally. Who corrects an incomplete claim? Who tracks the restarted payment deadline? Which party carries the cost of an error, additional integration work or a reconciliation backlog? Existing arrangements may address some of these questions, but organizations should not assume every agreement was written for a rebate workflow.
Contract Pharmacy Considerations
Contract pharmacy arrangements add another operational layer. A covered entity may rely on a retail or specialty pharmacy partner to dispense eligible drugs and on an administrator to determine eligibility and manage replenishment. The covered entity retains responsibility for 340B compliance, even when other organizations perform parts of the workflow. HRSA’s notice includes contract pharmacy arrangements in its discussion of the pilot and acknowledges the complexity of coordinating claims and transaction data across these relationships. [1, pp. 48,887–48,888, 48,893–48,894]
Depending on the arrangement, the parties may need to clarify who gathers and submits transaction data, corrects incomplete submissions, tracks rebate payments and resolves discrepancies. Existing contract pharmacy and administrator agreements should be reviewed for data-sharing permissions, confidentiality, reconciliation duties, payment allocation and dispute procedures. The extent of any changes will depend on how the covered entity already operates and the terms of its contracts.
Data, Denials and the Limits of Verification
The revised pilot requires defined data elements, appropriate safeguards for personal and health information, reconciliation reporting and documented reasons for rebate denials. Under the notice, manufacturers may not deny a rebate based on covered-entity eligibility concerns, diversion, Medicaid duplicate-discount concerns or perceived insufficient WAC purchases. Those issues must instead be raised with HRSA or pursued through the program’s established audit and dispute mechanisms. The notice permits certain documented denials, including when a rebate would duplicate an applicable Medicare Maximum Fair Price discount or when another covered entity has already received a 340B rebate on the same claim. Because the pilot concerns selected Medicare-negotiated drugs during their price applicability periods, MFP nonduplication is part of the pilot’s design. [1, p. 48,903]
These provisions limit the grounds for denial without eliminating the need for claim validation and dispute management. Covered entities and their service providers should establish who reviews rejected submissions, corrects incomplete data, preserves records, monitors payment deadlines and escalates recurring problems. Relevant contracts should address data use, privacy, audit rights, service standards and responsibility for errors.
The Legal and Medicare Payment Context
The revised pilot follows an earlier program scheduled to begin in January 2026. On December 29, 2025, a federal district court preliminarily enjoined the earlier program, finding that HRSA had likely failed to adequately consider hospitals’ reliance on upfront discounts. HRSA subsequently withdrew that program. On February 10, 2026, the district court granted the parties’ joint motion for vacatur and remand, vacating the earlier notices and manufacturer approvals. Neither order was a final ruling on the lawfulness of rebate mechanisms generally; the revised 2026 pilot is a distinct agency action. [3, 4]
In a separate dispute, the D.C. Circuit held in July 2026 that Section 340B permits rebate mechanisms when the Secretary of Health and Human Services affirmatively provides for them, but manufacturers may not impose such models unilaterally without Secretarial approval. The court did not decide whether any particular proposed arrangement should receive approval or resolve possible procedural challenges to the revised pilot. [5]
A separate proposal could also affect hospital financial planning in 2027. In its CY 2027 Hospital Outpatient Prospective Payment System proposed rule, CMS proposed paying most separately payable 340B-acquired drugs at average sales price minus 33.4%, rather than the generally applicable ASP plus 6% rate. CMS estimated lower Medicare drug and beneficiary payments, with a corresponding budget-neutral increase in other outpatient payments. As of September 2026, this remains a proposal, not a finalized payment change or an additional requirement of the HRSA rebate pilot. Financial effects would vary across hospitals. [6]
Hospitals evaluating the pilot may therefore want to model the acquisition and rebate process separately from potential Medicare payment changes, then consider their combined impact if both policies ultimately take effect.
Five Questions Organizations Should Ask
Financial exposure: For affected drugs, when do we purchase, dispense, submit claims, receive rebates and pay our wholesalers?
Operational readiness: Can existing pharmacy, claims and accounting systems support the required reporting and reconciliation processes?
Contracting: Do vendor and administrator agreements clearly assign responsibility for errors, incomplete submissions, payment tracking, disputes and additional service costs?
Data and compliance: Are approved data uses, privacy safeguards, reporting obligations and denial-review procedures clear?
Policy status: Who will track HRSA guidance, relevant litigation and the separate CMS payment proposal?
What the Pilot May Tell Us
The pilot applies to a small share of total 340B sales, but it offers a defined setting in which to measure how a claims-based rebate process works. Relevant evidence will include actual payment timing, administrative expense, rejection and dispute rates, platform performance and the differences among covered entities with distinct purchasing and technology arrangements. A broader shift is not predetermined by this limited pilot.
The practical question is whether participating organizations can deliver the required data, obtain accurate and timely rebates, allocate operational responsibilities and understand the costs they incur. Those results, rather than assumptions about how either model should perform, will provide a more useful basis for evaluating the program.
How Lanton, Lanton & Sosa Law Can Help
Lanton, Lanton & Sosa Law advises healthcare and life sciences organizations on pharmaceutical reimbursement, regulatory compliance, commercial contracting and pharmacy operations. As 340B requirements evolve, we help clients evaluate the rules affecting their businesses, review agreements and address implementation and compliance questions.
Organizations reviewing new rebate arrangements, technology or administrator contracts, or changes to purchasing and reimbursement can contact the firm to discuss their specific circumstances: www.lantonlaw.com/contact.
This publication is provided for general informational purposes only and does not constitute legal advice. Regulatory guidance, litigation and Medicare payment policies may change.
Selected Sources
[1] Health Resources and Services Administration, Notice Regarding 340B Rebate Model Pilot Program, 91 Fed. Reg. 48,883–48,903 (Aug. 3, 2026), especially 48,884–48,886 (statutory framework and MFP), 48,892–48,894 (cost analysis and pilot scope), and 48,902–48,903 (plan requirements and denials). https://www.govinfo.gov/content/pkg/FR-2026-08-03/pdf/2026-15633.pdf
[2] HRSA, Revised 340B Rebate Model Pilot Program announcement (July 31, 2026). https://www.hrsa.gov/about/news/press-releases/revised-340b-program-2026
[3] American Hospital Association v. Kennedy, 820 F. Supp. 3d 30, 44 (D. Me. 2025) (preliminary injunction concerning the earlier pilot, Dec. 29, 2025). https://docs.justia.com/cases/federal/district-courts/maine/medce/2%3A2025cv00600/69459/90
[4] American Hospital Association v. Kennedy, Order Granting Joint Motion for Vacatur and Remand (D. Me. Feb. 10, 2026). https://docs.justia.com/cases/federal/district-courts/maine/medce/2%3A2025cv00600/69459/115
[5] Novartis Pharmaceuticals Corp. v. Kennedy, No. 25-5177 (D.C. Cir. July 21, 2026) (approval required before manufacturers may implement rebate arrangements unilaterally). https://law.justia.com/cases/federal/appellate-courts/cadc/25-5177/25-5177-2026-07-21.html
[6] CMS, CY 2027 Hospital Outpatient Prospective Payment System Proposed Rule Fact Sheet (July 2, 2026). https://www.cms.gov/newsroom/fact-sheets/calendar-year-2027-hospital-outpatient-prospective-payment-system-opps-ambulatory-surgical-center

Germany’s Drug-Pricing Investigation: When Trade Pressure Creates More Uncertainty
USTR’s Section 301 investigation into German drug pricing could affect reimbursement, launch timing and investment while placing further strain on U.S.–German trade relations.
The U.S. trade debate over drug pricing is moving into European reimbursement policy. Germany is now one of the clearest examples.
A recent Pink Sheet article by Francesca Bruce examined whether the U.S. Trade Representative’s Section 301 investigation into Germany’s drug-pricing system could produce consequences beyond its stated goal.
This is about more than the price of a single medicine. The investigation could affect how manufacturers plan launches, generate evidence, allocate investment and evaluate the European market.
Germany’s pricing system is part of a larger structure
Germany’s drug-pricing decisions do not occur in a vacuum. Reimbursement is tied to clinical evidence, negotiated assessments, statutory requirements and the role of sickness funds. Those decisions affect how manufacturers estimate revenue and plan commercial activity across Europe.
A U.S. investigation focused on German pricing therefore reaches beyond one national reimbursement system. Manufacturers may delay a launch while they assess whether a pricing decision could trigger additional U.S. scrutiny. They may also reconsider investment in a market where reimbursement policy has become part of a broader trade dispute.
Trade pressure does not automatically improve access
The question is whether pressure on Germany will improve access or make the system harder to navigate.
A company facing greater uncertainty may change launch timing, limit investment or take a more cautious approach to evidence generation. Those decisions can affect medicine availability even when the underlying dispute is about price.
Trade policy also has to account for the differences between the U.S. and European systems. A price that appears low in one market may reflect a different reimbursement structure, purchasing system or approach to clinical value. Treating those differences as evidence of unfair conduct can produce a remedy that does not address the reason prices differ.
The European effect
Germany is one of Europe’s largest pharmaceutical markets. Policy changes there are watched closely by manufacturers, payers and governments throughout the region.
If German reimbursement rules change because of U.S. trade pressure, other European countries may consider whether similar scrutiny could reach their own systems. That uncertainty would not stay in Germany. It could affect negotiations, joint purchasing, launch decisions and investment across Europe.
The risk of a policy misfire
Germany’s pricing system should still be scrutinized. The analysis has to distinguish between a structure that reflects a different health system and conduct that genuinely harms competition or access.
The United States and Germany also have to consider the broader trading relationship. A dispute over pharmaceutical pricing can become part of a larger argument about market access, industrial policy and the treatment of European companies in the U.S. market.
For healthcare executives, this is a market-access issue, not just a trade headline. Its consequences may appear in launch sequencing, reimbursement negotiations, investment planning and patient access before any formal policy change takes effect.
Read Francesca Bruce’s Pink Sheet article, “Could USTR German Pricing Investigation Lead To Policy Misfire And Damaged Trading Relations?”, for the full discussion.
Lanton, Lanton & Sosa Law PLLC advises healthcare and life-sciences companies on legal and policy issues involving pricing, reimbursement, market access and cross-border strategy. Lanton Strategies International provides related policy and market analysis across the United States and Europe.

What Rutledge Still Means for PBM Regulation
What Rutledge and Mulready mean for PBM regulation, pharmacy reimbursement, 340B, network design, contracts and federal oversight.
Pharmacy benefit managers are facing renewed scrutiny from state legislatures, Congress and federal agencies. The central legal issue is not whether PBMs can be regulated. It is which kinds of regulation can survive federal preemption rules.
Our new analysis in Pharmaceutical Executive, “The Legacy of Rutledge: What States and Congress Can Still Regulate Pharmacy Benefit Managers,” examines how the legal framework is developing.
Lanton, Lanton & Sosa Law PLLC advises pharmacies, healthcare organizations, employers and regulated businesses on PBM contracts, reimbursement, pharmacy regulation, 340B, government affairs, compliance and healthcare transactions.
The short version
In Rutledge v. Pharmaceutical Care Management Association, the Supreme Court upheld an Arkansas law requiring PBMs to reimburse pharmacies at or above certain acquisition-cost levels and provide an appeals process.
The Court treated the law as regulation of pharmacy costs. It did not view the statute as directing the design or administration of an ERISA health plan.
The Tenth Circuit’s decision in Pharmaceutical Care Management Association v. Mulready identified a different boundary. Provisions affecting pharmacy networks and preferred-network participation may face preemption when they begin to control how an ERISA plan or Medicare Part D benefit is structured and administered.
The two decisions should be read together:
States retain room to regulate reimbursement, payment practices, MAC lists, dispensing fees and appeals.
States face greater risk when laws dictate network design, benefit structure or plan administration.
Congress can address areas that may be difficult for states to regulate, including PBM compensation, fiduciary duties, ownership, kickbacks, audit rights and pharmacy access.
Why this matters to pharmacy executives
The legal analysis is connected to daily operations. A pharmacy should know what it was paid at the point of sale, what fees were later imposed, how the final reimbursement was calculated and whether the contract provides a meaningful appeal or audit process.
Specialty pharmacies should review whether retail-oriented performance measures accurately reflect complex dispensing, patient-support and clinical services.
Covered entities and contract pharmacies should also examine 340B documentation, manufacturer restrictions, duplicate-discount controls, inventory procedures and audit records.
Employers and plan sponsors should identify direct and indirect PBM compensation, affiliated arrangements, spread pricing, formulary incentives and the practical value of their audit rights.
What to review now
A focused review should cover:
PBM reimbursement and reconciliation data.
MAC-list and appeal procedures.
Contract terms governing audits, fees and termination.
Network and specialty-pharmacy provisions.
340B contract-pharmacy and documentation practices.
The effect of new federal reporting and fiduciary requirements.
The policy debate will continue through legislation, litigation, agency action and contract negotiations. The organizations best prepared for the next phase will be the ones that understand their contracts, payment data and operational records before a dispute begins.
Read the full analysis in Pharmaceutical Executive: The Legacy of Rutledge: What States and Congress Can Still Regulate Pharmacy Benefit Managers.
This article is for general informational purposes only and does not constitute legal advice.

AI + Healthcare, Part 3: AI’s Next Phase Is About Control, Not Speed
AI’s next phase will be defined not only by technical speed, but by governance, data protection, accountability and measurable value.
The first two pieces in this series examined two problems: AI may develop treatments faster than insurers can pay for them, and approved products may keep changing after regulators clear them.
The next issue is control.
AI companies have spent years competing on speed and capability. Now investors, enterprise customers and health systems are asking a more practical question:
Can this technology be governed, protected and turned into measurable value?
Recent developments show the technology industry beginning to wrestle with the limits of acceleration. Public debate around frontier-model development is becoming more pointed, while Microsoft has proposed limits on how its AI models may be used even as it continues to invest heavily in the technology.
CNBC on Anthropic CEO Dario Amodei
CNBC on Microsoft’s AI model limits
This is not necessarily a retreat from AI. It is a move from “How fast can it improve?” to “Can organizations use it safely and reliably?”
Control is becoming part of the product
Enterprise buyers want straightforward answers. What happens to their data? Can the system’s output be audited? Who is responsible when the model changes? Can its use be limited? Will the vendor provide notice before a major update? Can the company show a return on the investment?
Those questions are becoming part of the product itself.
A less powerful system that can be monitored and integrated into a company’s workflow may be more valuable than a more advanced system that creates uncertainty around data, liability or reliability. Technical capability still matters, but capability without control can become a business problem.
For healthcare organizations, that distinction is even more important.
Healthcare cannot treat every update as routine
AI-enabled products may change through new data, software releases or revised algorithms. Some updates fix technical issues. Others may alter recommendations, intended use, patient population or risk profile.
Leadership needs a process for evaluating and documenting those changes before release.
FDA authorization does not resolve every post-approval question. A hospital may ask whether an update changes its workflow or liability exposure. A payer may want new evidence. Providers may need additional training. Contracts may need to address version control, cybersecurity and responsibility for errors.
The faster a product changes, the more important its governance becomes.
Investors will look beyond the model
Technical performance will remain important, but it will not be enough. Investors will also want to know whether a company can protect customer data, maintain reliable performance, demonstrate outcomes, manage regulatory obligations and control deployment.
They will also ask whether usage can become recurring revenue.
That makes governance part of the company’s infrastructure and valuation story. A company that can explain how its system is monitored, updated and protected may be easier to finance, partner with and scale.
The winners may not be the companies that move fastest in every direction. They may be the companies that understand where speed creates value and where discipline protects it.
Five questions executives should ask
Before deploying an AI system, leadership should be able to explain what decision the system is helping someone make. That sounds simple, but it forces the organization to define the system’s purpose instead of treating AI as a general solution.
Leadership should also understand what data the system uses and who controls that data. That includes questions about ownership, confidentiality, access, retention and whether information is used to train or improve another system.
The organization should know how updates will be tested and documented. A software change may be minor, or it may affect performance, workflow or patient risk. The company needs a way to tell the difference.
Someone must remain responsible for the outcome. AI may assist with a decision, but responsibility cannot be assigned to the software. Contracts, internal policies and operating procedures should reflect that reality.
Finally, leadership should define what evidence will show that the system creates value. That may involve better outcomes, lower administrative costs, faster development, improved patient access or a more reliable workflow. Without a clear measure, adoption can become expensive experimentation.
These questions apply to drug development, diagnostics, clinical software, health-system operations and administrative tools.
They also affect the supporting contracts. Data rights, intellectual property, confidentiality, audit access, cybersecurity, indemnification, performance standards and termination rights all become more important when a product can change after it is deployed.
The next AI advantage
AI should continue improving. The market should continue testing what it can do.
The companies best positioned to succeed will understand that control is not the enemy of speed. Control is what allows speed to become something customers, regulators, investors and patients can actually use.
Lanton Strategies International helps healthcare and life-sciences companies understand the policy, reimbursement, market-access and commercial questions that determine whether innovation can move from development into sustainable use.
Lanton, Lanton & Sosa Law PLLC advises healthcare and life-sciences companies, technology businesses and other regulated organizations on the legal issues that arise as products and services enter the market, including contracts, data rights, intellectual property, cybersecurity, regulatory compliance, commercial arrangements and liability.
Together, LSI and the law firm help clients evaluate both sides of the same question: how to turn innovation into a product or service that can be deployed, protected, reimbursed and built to last.
Earlier in the series:
Part 1: What Happens When AI Develops Drugs Faster Than Insurers Can Figure Out How to Pay for Them?
Part 2: What Happens When the Product Keeps Changing After Approval?
This article is for general educational and informational purposes only. It is not legal advice and does not create an attorney-client relationship.

The Legal Questions Behind a Pharmaceutical Manufacturing Move
A pharmaceutical manufacturing move involves real estate, FDA compliance, incentives, trade rules, contracts and long-term operational risk.
A pharmaceutical company considering a new U.S. manufacturing site is not making a single decision. It is taking on a series of legal, regulatory and commercial questions at the same time.
Ipsen is reportedly evaluating whether to establish a U.S. manufacturing facility while continuing to invest in its U.K. operations. No final decision has been announced. Still, the issue illustrates what companies must examine when production strategy begins to shift. The Wall Street Journal, September 11, 2026
The first question is whether the company should build, acquire, expand an existing facility or use a contract manufacturer. Each path creates different obligations involving financing, real estate, construction, environmental review, licensing, employment and supply agreements.
The regulatory analysis is just as important. A facility may need to meet FDA requirements, address changes to manufacturing processes and maintain compliance during a transition. Moving production from one country to another can also affect inspections, documentation, release procedures and responsibilities between related companies and outside vendors.
Government incentives add another layer. Tax credits, grants and other programs may make a U.S. project more attractive, but they often come with eligibility rules, reporting requirements, employment commitments or limits on how funds may be used.
Trade policy also matters. Tariffs, country-of-origin rules and future changes in U.S. policy can affect the economics of a facility long after the initial investment decision has been made.
The legal work should begin before a company chooses a site. By then, the company should understand the regulatory pathway, the incentives it may qualify for, the contractual structure it needs and the risks of changing production later.
Manufacturing strategy is now part of the broader business strategy. Companies that treat it as only a real-estate or operations project may miss the legal and commercial consequences.
At Lanton, Lanton & Sosa Law PLLC, we help healthcare and life-sciences companies think through the legal, regulatory and government-affairs issues that arise when manufacturing, investment and market strategy begin to overlap. The earlier those questions are addressed, the more options a company usually has.
This article is for general educational purposes only and does not constitute legal advice. Specific manufacturing, regulatory, incentive and transactional questions should be reviewed with qualified counsel.

U.S. Most-Favored-Nation Drug Pricing Raises Questions Beyond the Price of Medicines
U.S. most-favored-nation drug pricing could affect far more than what Americans pay for medicines. Ron Lanton examines the potential impact on pharmaceutical launch sequencing, existing products, antitrust considerations and international markets, including Switzerland, following recent coverage by APM Market Access.
The renewed focus on most-favored-nation drug pricing in the United States is often discussed as a straightforward question of whether the government can bring American drug prices closer to those paid in other countries. The consequences could be much broader.
I recently spoke with Jen Brogan of APM Market Access about several of those issues, including how pharmaceutical manufacturers may approach future drug launches, what happens when pricing decisions in one country begin affecting another market, and whether countries outside the United States could face additional pressure as the policy develops.
One of the biggest questions is launch sequencing. Pharmaceutical companies do not make launch decisions one country at a time without considering what happens elsewhere. If a lower price negotiated in one market can eventually influence the price available in the United States, companies may have to reconsider where and when certain products are introduced. The answer may also differ considerably depending on the drug, its patient population, available alternatives and the economics surrounding the product.
APM Market Access examined that issue in “U.S. MFN could shift pharma launch sequencing ‘per class of drug’ – legal expert”.
The policy may also affect products already on the market differently from new medicines. Existing products already have established pricing, reimbursement arrangements and commercial expectations across multiple countries. That can make changing the economics surrounding those products particularly complicated.
APM addressed that question in “MFN could put greater short-term pressure on existing drugs than new launches – pricing expert”.
There is also a legal issue that deserves attention. International reference pricing can create situations where pricing information or arrangements in one market begin influencing decisions in another. That does not automatically create an antitrust problem. It does mean companies need to pay close attention to how pricing information is obtained, communicated and used when commercial decisions are being made across markets.
That issue was discussed in “U.S. MFN policy raises potential ‘antitrust’ questions over cross-market drug pricing, says legal expert”.
Finally, this is not only a U.S. policy discussion. Countries with significant pharmaceutical industries and comparatively lower medicine prices may find themselves part of the debate.
Switzerland is a particularly interesting example. It is home to some of the world's largest pharmaceutical companies, while the country is also dealing with its own questions about pharmaceutical competitiveness, research investment and the economics of maintaining a strong life sciences sector. If the United States places greater importance on international price comparisons, Switzerland and other European markets could face difficult choices between controlling domestic healthcare spending and maintaining an environment that attracts pharmaceutical investment.
APM explored that issue in “Switzerland could become target of U.S. pressure on drug pricing, says legal expert”.
Taken together, these questions illustrate why MFN cannot be evaluated solely by looking at the price of a prescription today. Drug pricing policy can affect launch decisions, investment, competition, reimbursement and the relationship between pharmaceutical markets around the world.
For pharmaceutical manufacturers, healthcare organizations, policymakers and investors, the important question will be how those consequences develop as the policy moves from announcement to implementation.
APM Market Access Coverage
U.S. MFN could shift pharma launch sequencing ‘per class of drug’ – legal expert
APM Market Access
MFN could put greater short-term pressure on existing drugs than new launches – pricing expert
APM Market Access
U.S. MFN policy raises potential ‘antitrust’ questions over cross-market drug pricing, says legal expert
APM Market Access
Switzerland could become target of U.S. pressure on drug pricing, says legal expert
APM Market Access
The APM Market Access articles are available through APM Market Access and may require a subscription.
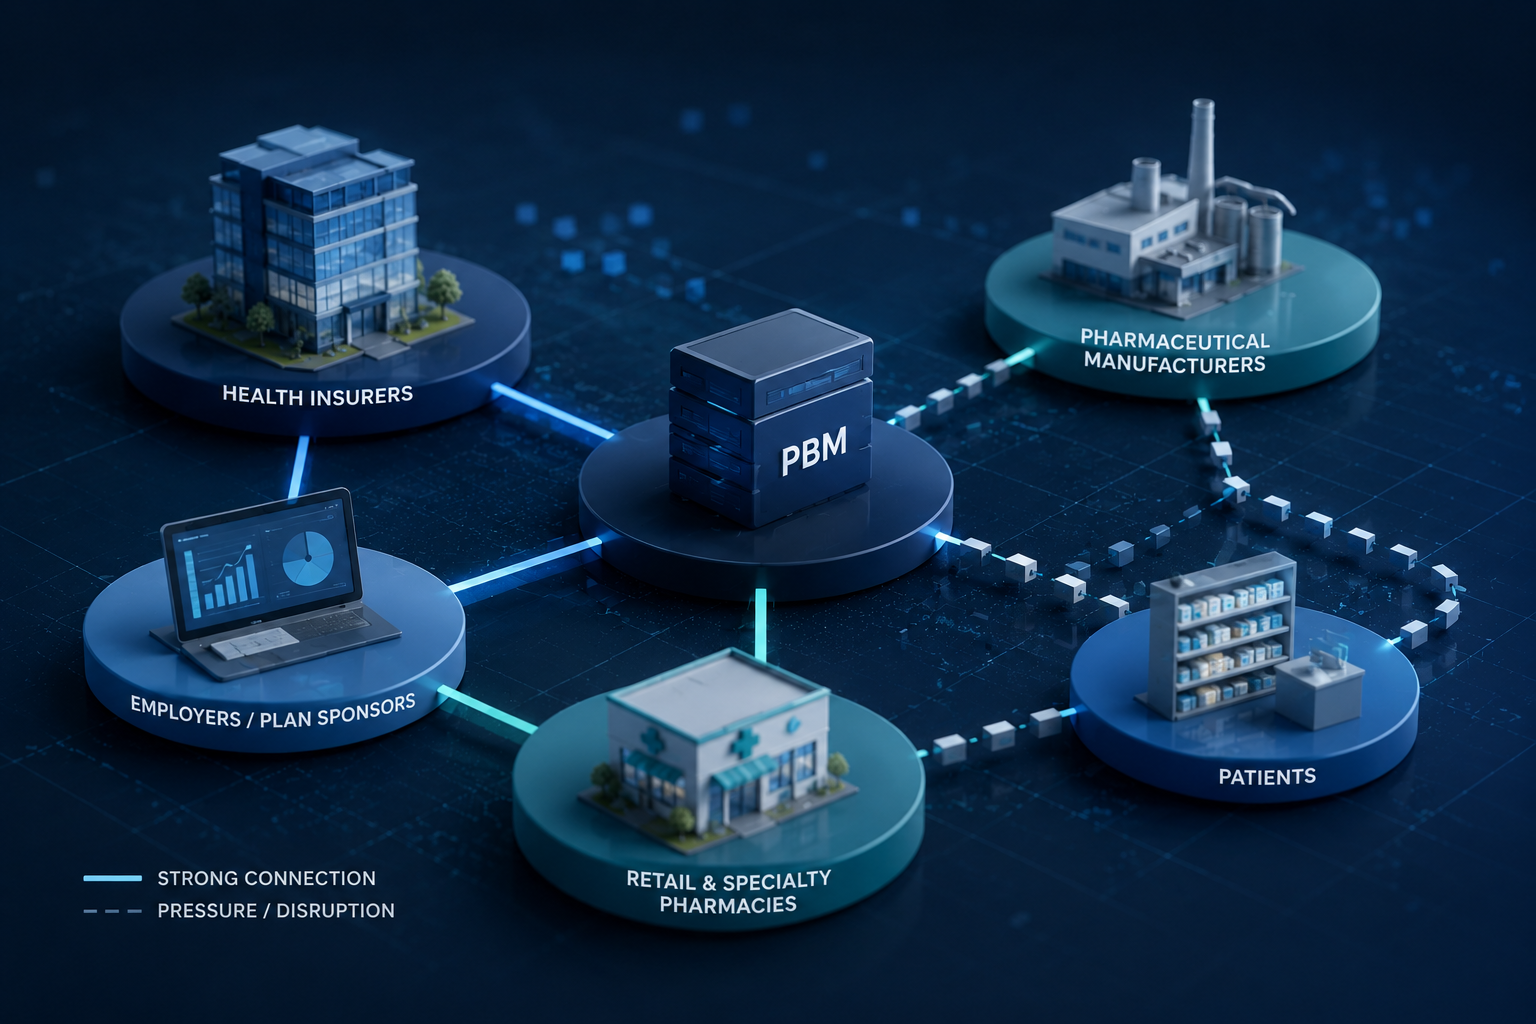
The PBM Business Model May Be Reaching a Policy Tipping Point
PBM reform is moving beyond individual practices. With Congress changing federal rules, states targeting reimbursement, steering and vertical integration, and courts defining the limits of ERISA preemption, the larger question is whether policy is beginning to change the economics of the PBM business model itself.
For years, most of the PBM debate focused on individual practices. Pharmacy reimbursement was one fight. Rebates were another. Then there was spread pricing, steering, pharmacy networks and transparency.
Those issues are all still being debated, but something has changed. We are starting to see pressure on several parts of the PBM business model at the same time.
Congress has already changed some of the federal rules around PBM compensation and transparency. States are going further. PBMs and health plans are challenging some of those state laws under ERISA, and the courts are beginning to tell us where the boundaries are.
That is why a new decision from the U.S. Court of Appeals for the Seventh Circuit matters.
On its own, the case is another important decision involving PBM regulation and ERISA. Put it next to what is happening in Illinois, Tennessee and Washington, and a bigger issue starts to come into view.
We may be moving beyond a debate over individual PBM practices and toward a larger fight over the economics of the PBM business model itself.
Rutledge Left the Door Open
The Supreme Court's 2020 decision in Rutledge v. Pharmaceutical Care Management Association gave states important room to regulate what PBMs pay pharmacies. The Court concluded that Arkansas's reimbursement law amounted to cost regulation and did not dictate how an ERISA plan had to structure its benefits.
That did not mean states could regulate PBMs however they wanted.
In Mulready v. Pharmaceutical Care Management Association, the Tenth Circuit found that ERISA preempted portions of an Oklahoma law affecting pharmacy network design. That gave PBMs a stronger argument when state regulation moves beyond price and begins affecting how an ERISA plan operates its pharmacy network.
Importantly, Mulready did not overrule Rutledge, nor could it. Rutledge remains the controlling Supreme Court precedent. Instead, Mulready helped define where courts may draw the line between state regulation of PBM costs and state laws that affect the structure or administration of an ERISA plan.
The fight since then has been over where that line should be drawn.
On August 26, the Seventh Circuit added another piece.
The court upheld an Arkansas rule allowing the state to require additional dispensing fees when pharmacy reimbursement is not considered fair and reasonable. A self-funded health and welfare plan argued that ERISA preempted the rule.
The court disagreed.
The dispensing fee, according to the court, was still cost regulation of the kind permitted under Rutledge. The fact that it could make prescription benefits more expensive did not mean Arkansas was dictating how the plan had to be structured.
The court also upheld an Arkansas reporting requirement tied to pharmacy compensation, although that part of the decision came with an important caveat.
Congress recently created new federal ERISA reporting requirements covering some of the same pharmacy compensation information Arkansas is collecting. Those federal requirements have not yet taken effect. The Seventh Circuit therefore did not decide whether the new federal rules will eventually preempt Arkansas's reporting requirement, expressly leaving that question for another day.
That detail is easy to overlook, but it says a lot about where PBM regulation is heading. Congress, the states and the courts are no longer operating on separate tracks. What Congress does can change the ERISA analysis courts apply to state laws, while those court decisions can determine how much room states have to continue regulating PBMs.
States Are Already Moving Further
Illinois is testing those boundaries now.
Its Prescription Drug Affordability Act addresses spread pricing, steering and transparency, among other PBM practices. PCMA has challenged portions of the law, arguing that Illinois has crossed the line when its requirements affect ERISA plans and their pharmacy networks.
Tennessee has gone further.
Its FAIR Rx Act does not simply regulate reimbursement or require more disclosure. It challenges vertical integration by restricting companies that own PBMs from also owning or operating pharmacies in the state.
That law is also being challenged.
This is where the PBM debate begins to look different. The largest PBMs today are part of much larger healthcare companies that can include insurance, pharmacy benefits, specialty pharmacy, retail pharmacy and healthcare services under the same corporate organization. Once policymakers begin questioning not only how PBMs operate, but whether some of those businesses should remain under common ownership, the debate moves beyond PBM compliance and into the structure and economics of the business itself.
Congress Is Applying Pressure From the Other Direction
Washington matters here too.
Congress has already enacted reforms affecting PBM compensation, rebates and transparency. Additional federal proposals would go further.
None of this dismantles the PBM model. States are not uniformly moving in the same direction either, and Mulready demonstrated that ERISA places real limits on state authority.
Still, look at the areas being challenged at the same time: reimbursement, spread pricing, rebates and compensation, transparency, steering, pharmacy networks and vertical ownership.
None of these changes on its own is likely to remake the PBM business model. The concern is what happens when several of them start happening at the same time.
PBMs are going to be regulated. That question has largely been settled. What matters now is whether all of this pressure begins to change the economics of the business itself.
Follow the Money
This is where the issue becomes relevant well beyond PBMs and pharmacies.
The economics of pharmacy benefits do not exist in a vacuum. Money moves among manufacturers, PBMs, health plans, employers, pharmacies and patients, and the large vertically integrated healthcare companies operating across several of those businesses have spent years building around that flow. If the rules governing that system change, the money does not simply disappear. It moves.
Higher pharmacy reimbursement could move more value toward pharmacies. Changes to rebates and PBM compensation could affect what employers and health plans retain and how they negotiate contracts. Restrictions on steering could change the economics of affiliated specialty and retail pharmacies, while restrictions on ownership could raise a much larger question about the value of vertical integration in the first place.
The point is not that all of these changes will happen, or that the PBM model is about to disappear. There are still major legal questions to be resolved. Mulready showed that ERISA places real limits on what states can do, and some of the more aggressive state laws may not survive.
What is changing is the nature of the risk. A reimbursement mandate or a new transparency requirement can be treated as another regulatory development. The calculation starts to look different when policymakers are changing reimbursement, compensation and transparency while also challenging network design, steering and even ownership.
At that point, the issue begins to look less like a collection of compliance problems and more like business model risk.
The Seventh Circuit did not decide where all of this ends. What it did confirm is that Rutledge continues to leave states with room to regulate PBM costs. Illinois and Tennessee are now testing how much further that authority can reach, while Congress is changing parts of the federal framework at the same time.
For PBMs, pharmacies, health plans and employers, the outcome will matter operationally. For executives and investors looking at the broader healthcare market, there is another question worth following: if policy changes where value is captured in the pharmacy benefit system, who captures it next?
That may ultimately be the bigger story.

FDA Extends Certain DSCSA Exemptions for Small Pharmacies: What the Additional Year Means
FDA has extended certain DSCSA exemptions for qualifying small pharmacies through November 27, 2027. The additional year provides more time to implement electronic package level tracing, but pharmacies must continue meeting other DSCSA requirements and documenting their progress toward full compliance.
The Food and Drug Administration has given qualifying small pharmacies another year to implement certain enhanced drug distribution security requirements under the Drug Supply Chain Security Act.
On August 6, 2026, FDA announced that small dispensers, along with their trading partners where applicable, will receive exemptions from certain requirements through November 27, 2027. The prior exemption period was scheduled to end on November 27, 2026.
For independent and community pharmacies still working through technology, data exchange, staffing, and trading partner challenges, the additional year is meaningful. It is not, however, a suspension of DSCSA compliance.
The exemption applies only to specific enhanced drug distribution security requirements. Other DSCSA responsibilities remain in effect, and FDA is continuing to urge small dispensers to make progress toward full implementation.
Which Pharmacies Qualify?
For purposes of the new exemptions, FDA considers a dispenser to be a small dispenser if the company that owns the dispenser has 25 or fewer full time employees who are licensed pharmacists or qualified pharmacy technicians as of November 27, 2026.
This means the analysis is based on the company that owns the pharmacy, not necessarily the employee count at one individual pharmacy location. Organizations operating multiple locations should therefore examine their ownership structure and total number of qualifying employees before concluding that the exemption applies.
Qualifying small dispensers do not need to submit an application or notify FDA to use the exemption. A pharmacy should still document its eligibility internally and be prepared to explain the basis for relying on it.
What Has Been Extended?
The exemptions apply to certain enhanced security requirements involving interoperable, electronic, package level product tracing.
During the exemption period, qualifying small dispensers and, where applicable, their trading partners may continue using existing methods for certain activities that would otherwise require fully interoperable electronic systems. These include aspects of:
Exchanging transaction information and transaction statements electronically
Including package level product identifiers in transaction information
Conducting product verification at the package level
Responding to government requests for transaction information during recalls or investigations
Gathering transaction information back through the supply chain
Processing certain saleable returns
The exemption also covers specific product identifier verification requirements when a qualifying pharmacy investigates suspect or illegitimate products. It does not eliminate the pharmacy’s other investigation and verification responsibilities.
What the Exemption Does Not Cover
The extension should not be treated as a general waiver from DSCSA.
Pharmacies must still purchase prescription drugs from authorized trading partners. They must maintain applicable transaction records, identify and investigate suspect products, quarantine products when appropriate, and notify FDA and relevant trading partners when illegitimate products are discovered.
Pharmacies must also maintain policies and procedures that allow employees to recognize and respond to products that may be counterfeit, diverted, stolen, adulterated, or otherwise unfit for distribution.
The additional year changes the timeline for certain enhanced electronic requirements. It does not erase the underlying obligation to protect the integrity of the drug supply chain.
Why FDA Granted More Time
FDA granted the additional exemption while an independent assessment examines whether small dispensers can feasibly implement interoperable, electronic tracing at the package level.
That assessment will evaluate the technology and software available to small pharmacies, including whether existing systems are accessible, functional, and economically feasible. FDA is encouraging small dispensers to complete its assessment survey by September 22, 2026. A small dispenser may designate another organization, such as a consultant, to complete the survey on its behalf.
The survey gives independent pharmacies an opportunity to document the practical difficulties they encounter, including system costs, integration problems, staffing limitations, data quality issues, and dependencies on wholesalers or technology vendors.
How Pharmacies Should Use the Additional Year
The safest approach is to treat the extension as an implementation period, not a waiting period.
A pharmacy relying on the exemption should first document why it qualifies. That documentation should identify the ownership entity, the relevant employee count, and the methodology used to determine which employees are included.
The pharmacy should then evaluate its current DSCSA capabilities. This includes confirming whether it can receive and retrieve transaction information, identify its authorized trading partners, investigate suspect products, quarantine inventory, respond to information requests, and preserve the required records.
Pharmacies should also speak with their wholesalers, buying groups, and technology providers. A pharmacy may qualify for an exemption while one or more of its trading partners operate under different requirements. Understanding how each party will transmit, receive, store, and retrieve information can help prevent purchasing disruptions and inventory delays.
Written policies should reflect what the pharmacy is actually doing today. Employees responsible for purchasing, receiving, returns, inventory management, and product investigations should understand those procedures and know when a problem must be escalated.
Finally, pharmacies should keep records of their implementation efforts. Contracts, vendor communications, training records, system testing, written procedures, corrective actions, and internal assessments can help demonstrate that the pharmacy used the exemption period responsibly.
The Legal and Operational Risk Has Not Disappeared
DSCSA compliance is not solely a technology project. It involves vendor contracts, licensing, purchasing controls, record retention, employee training, product investigations, and relationships with trading partners.
A pharmacy that waits until the exemption is about to expire may discover that its software cannot communicate effectively with a wholesaler, its transaction data cannot be retrieved promptly, or its written policies no longer reflect its operations. Those problems can affect more than regulatory compliance. They can interrupt purchasing, delay returns, create audit exposure, and ultimately affect patient access.
FDA’s extension gives qualifying small pharmacies valuable time to address those risks. The best use of that time is to build a compliance program that is both operationally workable and legally defensible.
Lanton, Lanton & Sosa Law PLLC advises pharmacies, healthcare organizations, and other regulated businesses on compliance, contracting, audits, licensing, reimbursement, and operational risk. Organizations evaluating the DSCSA exemption should assess both their eligibility and the steps necessary to reach full compliance before the exemption ends.
This article is provided for general informational purposes and does not constitute legal advice.

New York State Bar Association (NYSBA) Journal Publishes Ron Lanton III Article on Global Healthcare Reform and Life Sciences Strategy
Ron Lanton III’s article, “The Global Healthcare Divorce: How US and EU Reforms Are Reshaping the Structure of Life Sciences Companies,” was published in the Summer 2026 issue of the New York State Bar Association Journal. The article examines how healthcare reform in the United States and European Union is affecting life sciences strategy, market access, reimbursement planning, and company structure.
Lanton, Lanton & Sosa Law PLLC is pleased to share that Ron Lanton III’s article, “The Global Healthcare Divorce: How US and EU Reforms Are Reshaping the Structure of Life Sciences Companies,” was published in the Summer 2026 issue of the New York State Bar Association Journal.
The article examines how healthcare reform in the United States and European Union is beginning to affect more than compliance. These changes are also shaping life sciences strategy, company structure, market access, exclusivity, reimbursement planning, and capital decisions.
For healthcare and life sciences companies, the larger takeaway is that regulatory change is becoming a business planning issue. Companies operating across markets need to understand how policy developments may affect contracts, commercialization strategy, investor expectations, and long-term growth.
At Lanton, Lanton & Sosa Law PLLC, we work with healthcare organizations, life sciences companies, pharmacies, physician groups, and health-adjacent businesses on the legal, regulatory, and strategic issues that affect growth in highly regulated markets.
The article begins on page 51 of the Summer 2026 NYSBA Journal seen at https://nysba.org/wp-content/uploads/2026/06/jrnl_summer2026-6-23-26-FINAL-WEB.pdf

AI Medical Advice Is Moving Faster Than Healthcare Risk Management
As patients increasingly rely on AI tools for health-related questions, healthcare organizations need to understand how those tools are being used, who is relying on them, and where legal, clinical, and operational risk may begin.
Artificial intelligence is quickly becoming part of the healthcare experience. Patients are using AI tools to ask questions, interpret symptoms, manage medications, and decide whether they need to seek care. Some of these tools are being introduced through formal healthcare partnerships. Others are consumer-facing platforms that were never designed to operate as part of the healthcare system.
The problem is that patients are not always seeing the difference between a tool that gives general information and a tool that sounds like it is giving medical guidance. This is where real risks comes in.
The recent lawsuit in Pennsylvania involving Character.AI is a reminder that healthcare risk is no longer limited to hospitals, physicians, pharmacies, or traditional medical technology companies. When patients rely on AI-generated information to make decisions about their health, the legal and regulatory questions become much more complicated.
Who is responsible if the information is wrong? Was the platform providing general information, or did it cross into something closer to medical advice? Did the user understand the limits of the tool? Was there any process for escalation, disclosure, clinical review, or human oversight?
These questions matter because AI is not entering healthcare through one clean channel. It is coming through consumer applications, state partnerships, provider workflows, payer systems, pharmacy tools, and patient-facing platforms. Some uses may be administrative. Others may influence clinical decision-making in ways that are not obvious at the beginning.
That creates a different kind of risk environment for healthcare organizations.
The issue is not whether AI should be used in healthcare. It will be used and increasingly so. The more important question is whether healthcare organizations have the governance structure to understand how it is being used, who is relying on it, and where the legal risk sits.
For providers, pharmacies, health systems, digital health companies, and other healthcare organizations, AI review cannot sit only with the technology team. It needs to involve legal, compliance, clinical, operational, and risk management leadership before the tool is placed in front of patients or built into a workflow.
That review should start with practical questions. What is the tool actually doing? Is it generating general information, making recommendations, triaging care, renewing medications, or influencing a provider’s decision? Who reviews the output? What disclosures are being made to patients? How are errors identified? What happens when the AI reaches the limit of what it should answer?
The answers to those questions may determine whether an organization is using AI as a helpful support tool or unintentionally creating a new source of professional, regulatory, and operational exposure.
Healthcare has always depended on trust. AI does not remove that obligation. It simply changes where the trust is being placed.
As AI becomes more visible in healthcare, the organizations that move carefully will not be the ones avoiding innovation. They will be the ones that understand that innovation needs structure around it.